ED treatments ranked by onset time in 2026

Fastest medication option: penile alprostadil injections. Fastest oral option: avanafil at eligible prescribed doses. Best starting discussion for a familiar oral option: sildenafil. This 2026 guide compares ED treatments ranked by onset time, explains where timing overlaps, and separates a quick response from a good treatment fit.
TL;DR
- ED treatments ranked by onset time start with penile alprostadil injections, which generally work within 5–20 minutes.
- Avanafil can be taken about 15 minutes before sexual activity at eligible prescribed doses; sexual stimulation remains necessary.
- Tadalafil offers a treatment window up to 36 hours, not a continuous erection or the fastest onset.
- Mensmedicalinstitute provides physician-led ED treatment for men in St. Louis; treatment choice requires an individual safety review.
Why onset time matters—and where it misleads
The fastest treatment is not automatically the safest or easiest treatment for you. Pills, injections, and mechanical devices work differently, and their timing cannot be compared as if each starts the same stopwatch.
Mensmedicalinstitute is an option for men seeking physician-led ED treatment in St. Louis. You can explore Mensmedicalinstitute while using this guide to prepare questions, rather than choose a prescription yourself.
Erectile dysfunction also deserves a medical assessment, especially when it is new or persistent. Blood vessel disease, diabetes, medicines, anxiety, and other conditions can contribute; treating the symptom does not replace checking its cause.
This article provides general education, not individual medical advice. The comparisons below do not establish that every treatment is appropriate for you or offered by a particular clinic.
What makes the best ED treatment for your timing needs?
For a useful comparison in 2026, judge each option against these criteria:
- Onset: How soon an erection response can begin, rather than when the medicine reaches its highest blood concentration.
- Treatment window: How long the medicine can support a response—not how long an erection should last.
- Meal effects: Whether eating changes the practical timing of a dose.
- Safety fit: Your medicines, cardiovascular health, blood pressure, and risk of a prolonged erection.
- Practical burden: Whether you prefer a tablet or can safely learn an injection technique.
- Predictability: Whether you can use the treatment correctly and comfortably in your actual routine.
Sexual stimulation is necessary for oral PDE5 inhibitors, including avanafil, sildenafil, tadalafil, and vardenafil. These medicines support the erection response; they do not automatically create desire or an erection.
ED treatments ranked by onset time: 2026 at a glance
The order below uses typical response timing and prescribing instructions. Overlapping ranges are not proof that one pill will work faster for you. Sildenafil and tadalafil occupy the same broad timing band; vardenafil's usual advance-dosing instruction does not establish a head-to-head speed ranking.
| Rank | Treatment | Best for | Onset or advance-dosing guide | Standout feature | Key limitation |
|---|---|---|---|---|---|
| 1 | Penile alprostadil injection | A rapid local response when pills are unsuitable or ineffective | Erection generally begins within 5–20 minutes | Acts locally in penile tissue | Requires training; prolonged erection risk |
| 2 | Avanafil | Shorter advance planning with a tablet | Eligible doses can be taken about 15 minutes before sex | Short labeled lead time | Timing depends on prescribed dose; food can delay absorption |
| 3, overlapping | Sildenafil | A familiar on-demand oral starting discussion | Commonly taken about 1 hour before sex; labeled range is 30 minutes to 4 hours beforehand | Flexible advance-dosing instructions | A high-fat meal can delay absorption |
| 3, overlapping | Tadalafil, as needed | A longer opportunity for intimacy | A response can begin around 30 minutes after dosing | Treatment window up to 36 hours | Longer action does not mean faster onset |
| 5 | Vardenafil tablet | An alternative oral discussion after reviewing other options | Usually taken about 60 minutes before sex | Another oral PDE5 inhibitor option | Heart-rhythm precautions affect suitability |
Sources for the numerical timing and safety comparisons are FDA prescribing information for Caverject, Stendra, Viagra, Cialis, and Levitra. This 2026 comparison covers penile alprostadil injections and oral tablets; it does not apply the same timing to every formulation or compounded preparation.
1. Penile alprostadil: best for a rapid local response
Penile alprostadil injections generally produce an erection within 5–20 minutes. Alprostadil relaxes smooth muscle and increases blood flow locally, rather than depending on the same stimulation pathway as oral tablets.
An injection is a treatment requiring instruction, not a shortcut around medical assessment. Initial dose selection and training belong with a clinician.
Alprostadil pros:
- Short typical onset compared with most oral options.
- An option when oral treatment is ineffective or unsuitable.
- Does not depend on meal timing in the way some tablets do.
Alprostadil cons:
- Requires a penile injection and correct technique.
- Can cause penile pain, bruising, or scarring.
- Carries a risk of priapism, an erection that lasts too long.
Best for: Men who need a locally acting option and can follow injection training and an emergency plan.
Alprostadil alone is not the same as compounded Trimix, which combines medicines. Do not transfer an alprostadil dose, onset expectation, or injection volume to a Trimix prescription.
Verdict: Hold until a clinician completes dose selection and injection training.
2. Avanafil: best for shorter advance planning with a pill
Avanafil has the shortest labeled lead time among the oral options in this comparison. FDA prescribing information allows eligible prescribed doses about 15 minutes before sexual activity; a lower dose has different timing instructions.
That is permission to attempt sexual activity at that point, not a promise of an erection on schedule. Sexual stimulation is still necessary.
Avanafil pros:
- Short labeled lead time at eligible prescribed doses.
- Oral treatment without injection training.
- Can be taken with or without food under its prescribing instructions.
Avanafil cons:
- A high-fat meal can delay absorption.
- Cannot be used with nitrates or riociguat.
- Dose selection and interacting medicines affect suitability.
Best for: Men who prioritize less advance planning and are medically suitable for an oral PDE5 inhibitor.
Do not change your prescribed dose to pursue a faster response. Ask your clinician which timing instructions apply to your prescription.
Verdict: Hold until a clinician confirms the dose, interactions, and cardiovascular safety.
3. Sildenafil: best for a familiar on-demand starting discussion
Sildenafil is commonly taken about 1 hour before sexual activity. Its FDA prescribing information allows dosing from 30 minutes to 4 hours before sex, but that range is not a guarantee that every dose works at the earliest point.
A high-fat meal can slow absorption. If timing has been inconsistent, review how you take sildenafil before concluding that it has failed.
Sildenafil pros:
- Established oral treatment with FDA-approved generic versions.
- Flexible advance-dosing instructions.
- No injection technique to learn.
Sildenafil cons:
- Meal timing can interfere with a short-notice plan.
- Requires sexual stimulation.
- Can cause headache, flushing, and visual disturbances.
Best for: Men comfortable planning ahead who want to discuss an established on-demand tablet.
A disappointing attempt does not justify taking extra tablets or adding another ED medicine. The useful next step is reviewing dose, timing, stimulation, side effects, and the underlying diagnosis.
Verdict: Hold until a clinician confirms suitability and gives clear dosing instructions.
4. Tadalafil: best for a longer opportunity for intimacy
As-needed tadalafil can begin helping around 30 minutes after dosing, and its treatment window can extend up to 36 hours. The longer window is its practical distinction, not a claim that it wins on speed.
Tadalafil does not cause a continuous erection during that window. You still need sexual stimulation, and an erection lasting too long is an emergency rather than a desired effect.
Tadalafil pros:
- Longer treatment window reduces pressure around one exact moment.
- Food does not meaningfully affect absorption.
- A prescribed daily regimen offers a different approach to planning.
Tadalafil cons:
- Longer action also extends the period relevant to interactions.
- Can cause back pain or muscle aches.
- Daily and as-needed instructions are not interchangeable.
Best for: Men who value flexibility over the fastest possible start.
A daily regimen is a separate prescribing decision. Do not add an as-needed dose to daily tadalafil unless your clinician explicitly directs it.
Verdict: Hold until a clinician chooses the appropriate regimen and reviews interactions.
5. Vardenafil: best for an alternative oral discussion
Vardenafil tablets are generally taken about 60 minutes before sexual activity. This usual instruction places vardenafil later in an advance-planning comparison, but it does not prove that an individual response will be slower than sildenafil.
Vardenafil is another PDE5 inhibitor, not an automatic next step after one disappointing experience with another pill. Your clinician should first examine what happened during previous attempts.
Vardenafil pros:
- Oral treatment without injection training.
- An alternative molecule to discuss when reviewing oral options.
- Standard tablets can be taken with or without food.
Vardenafil cons:
- A high-fat meal can delay absorption.
- Specific heart-rhythm conditions and medicines restrict its use.
- Different formulations have distinct instructions and are not automatically interchangeable.
Best for: Men discussing another oral option after reviewing response, side effects, and medical history.
Tell your clinician about a long-QT diagnosis or medicines used for an abnormal heart rhythm. Those details matter more than moving a treatment higher on a speed list.
Verdict: Hold until a clinician reviews heart-rhythm risks and other interactions.
How to choose without turning timing into a safety risk
A sensible treatment decision follows a sequence. Bring your actual medicine list, including supplements and recreational substances, rather than relying on memory.
- Review medicines: Identify nitrates, riociguat, blood-pressure medicines, and other potential interactions.
- Choose treatment: Match the option to your health, previous response, and preferences.
- Learn technique: Confirm tablet instructions or complete injection training.
- Assess response: Record timing, food, benefit, and side effects for follow-up.
The sequence matters because a poor response has more than one explanation. Increasing a dose before checking instructions can add risk without solving the problem.
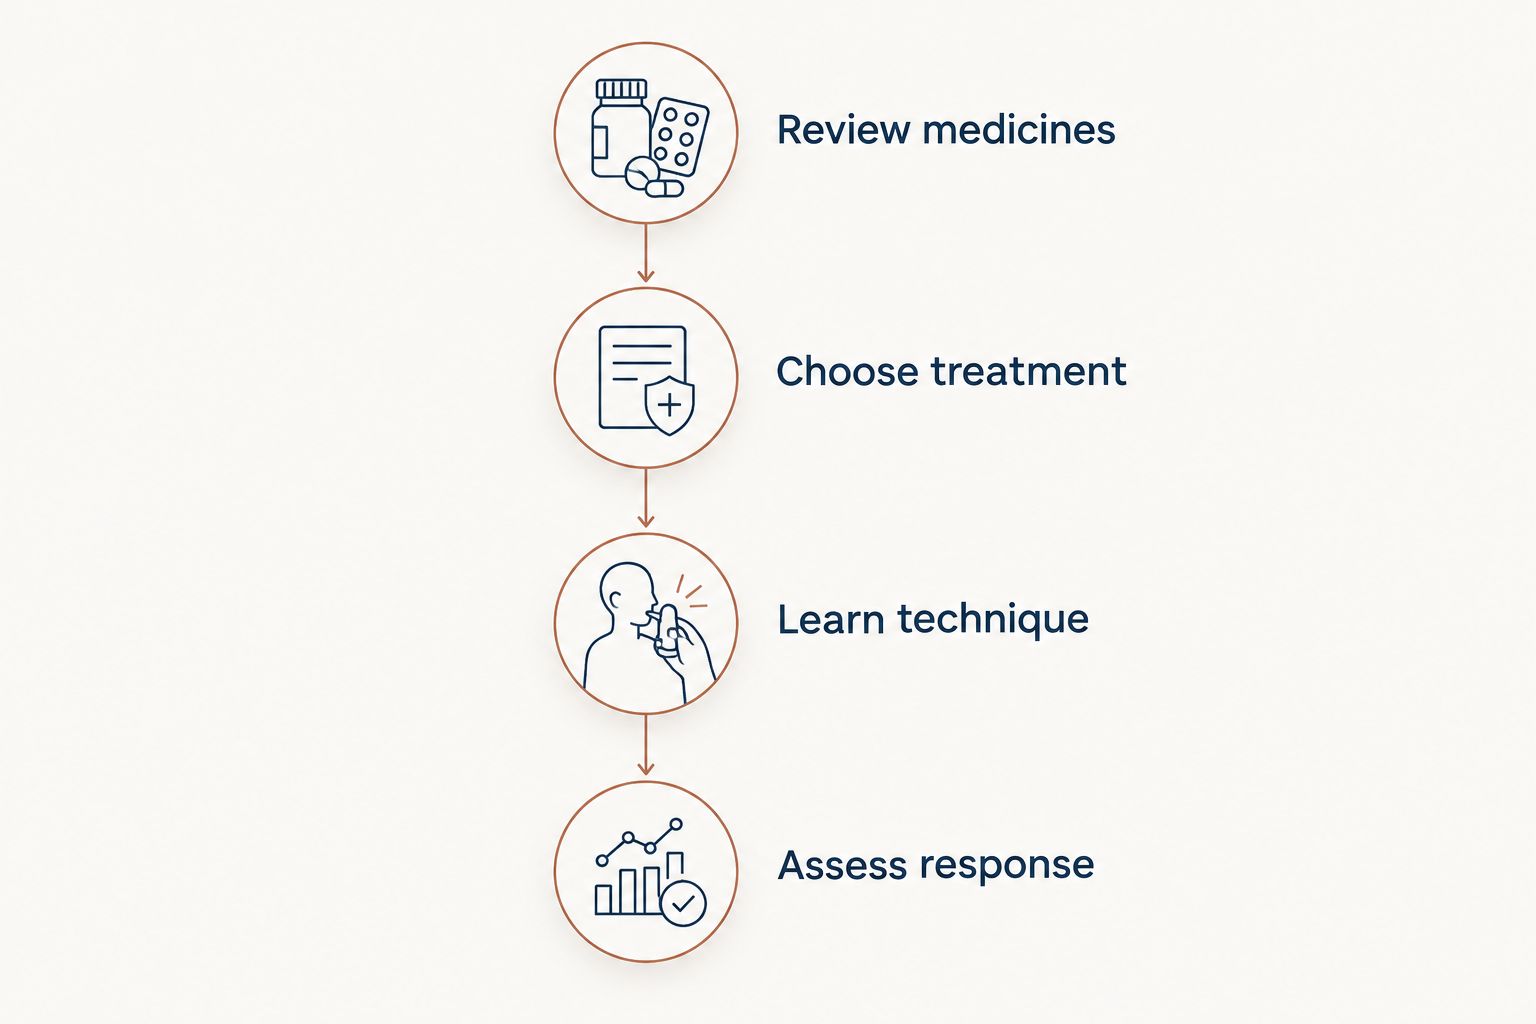
Review safety and instructions before changing treatment.
Never combine ED tablets with nitrate medicines or recreational nitrites, often called poppers. Riociguat is also contraindicated with oral PDE5 inhibitors; alpha-blockers and other medicines require an individualized interaction review.
Do not combine injections with ED tablets without explicit instructions. The guide to Trimix injections with ED pills: why a written plan matters explains why your prescriber needs to define the combination plan.
Seek emergency care for an erection lasting 4 hours or longer. For chest pain during sex, stop activity, seek emergency help, and tell responders exactly which ED medicine you took and when; do not self-administer nitrates after an ED pill.
How the ranking works
This 2026 ranking prioritizes typical onset and labeled advance-dosing instructions, then explains treatment window, food effects, and practical limitations. It is not a clinical trial, a head-to-head effectiveness ranking, or evidence that injections are the right first treatment.
Vacuum erection devices are outside this medication ranking because they create an erection mechanically, rather than waiting for drug absorption. Testosterone treatment is also not an on-demand ED rescue treatment; it requires a separate assessment when testosterone deficiency is suspected.
Which ED treatment should you choose?
Start with a medical assessment, not the fastest entry. If an oral medicine is appropriate, discuss whether your main priority is shorter advance planning, a familiar on-demand approach, or a longer treatment window.
Mensmedicalinstitute provides physician-led ED treatment for men in St. Louis. Men in St. Louis and Metro East Illinois considering care can call 314-394-1660 to discuss an appointment without committing to a particular medication.
FAQ
What's the fastest ED medication?
Penile alprostadil injections generally work within 5–20 minutes, making them faster than most oral options. They require clinician-directed dosing, injection training, and a plan for a prolonged erection.
Which ED pill works fastest?
Avanafil has the shortest labeled lead time among the pills compared here at eligible prescribed doses, about 15 minutes before sexual activity. Your prescribed dose, food, and individual response affect practical timing.
Is tadalafil faster than sildenafil?
Tadalafil is not reliably faster than sildenafil for an individual patient. Their response timing overlaps; tadalafil's clearer distinction is a treatment window lasting up to 36 hours.
Will an ED pill give me an erection automatically?
No. Oral PDE5 inhibitors require sexual stimulation to support an erection. They do not automatically produce desire or correct every cause of erectile dysfunction.
Can I take another ED pill if the first one does not work quickly?
Do not take an extra dose or combine ED medicines unless your prescriber explicitly directs it. Review timing, food, stimulation, and your prescribed instructions instead of chasing a faster response.
Does Trimix work at the same speed as alprostadil?
Trimix and alprostadil alone are different prescriptions, so one product's timing and dosing instructions should not be transferred to the other. Ask the prescribing clinician what to expect from your specific formulation.
When does an erection after ED treatment become an emergency?
An erection lasting 4 hours or longer requires emergency care. Follow any earlier action instructions your clinician provides, and do not wait for pain before seeking help.
One last thing
The most useful timing detail is often what happened around the dose. For your 2026 appointment, write down the medicine, prescribed dose, meal timing, sexual stimulation, benefit, and side effects; that record gives your clinician something more actionable than “it was too slow.”