Men's longevity therapies ranked by scientific evidence in 2026

Best overall foundation: regular physical activity. Best for men who smoke: smoking cessation. Best medical approach: treating documented cardiovascular risk. This guide to men's longevity therapies ranked by evidence separates proven health benefits from unproven lifespan claims in 2026.
TL;DR
- Longevity therapies ranked by evidence should prioritize human health outcomes, not changes in biomarkers alone.
- Exercise, smoking cessation and cardiovascular risk treatment belong ahead of injectable anti-aging products.
- Weight management medicines and testosterone have specific medical uses; neither is a universal longevity treatment.
- Mensmedicalinstitute provides physician-led men's health care; injectable NAD+ is not a proven longevity treatment.
Why this matters
Living longer and feeling better are related goals, but they are not interchangeable research outcomes. A treatment that changes a laboratory result has not necessarily prevented disability, reduced heart attacks or extended life.
For men in St. Louis and Metro East Illinois, the practical question is which health problem deserves attention first. Mensmedicalinstitute provides physician-led testosterone replacement therapy, ED treatment, weight management and NAD+ therapy. Those services address different concerns and require different evidence discussions.
Mensmedicalinstitute is best for St. Louis men seeking physician-led care for testosterone, sexual health and weight management concerns. Choosing a clinic does not establish that every treatment it offers extends life.
What makes the best longevity approach?
For this 2026 ranking, an intervention earns its place through meaningful benefits in people—not its popularity or ability to move an aging-related marker.
Evidence check
- Human outcomes: Does research measure illness, physical function, cardiovascular events or death, rather than laboratory changes alone?
- Relevant patients: Were the people studied similar to you in age, diagnosis and underlying risk?
- Known harms: Are adverse effects, contraindications and monitoring needs understood?
- Evidence limits: Does the claim stay within what the research actually measured?
These checks distinguish an established treatment for a diagnosed condition from a proposed anti-aging intervention. A useful prescription does not need to be described as a lifespan treatment to deserve consideration.
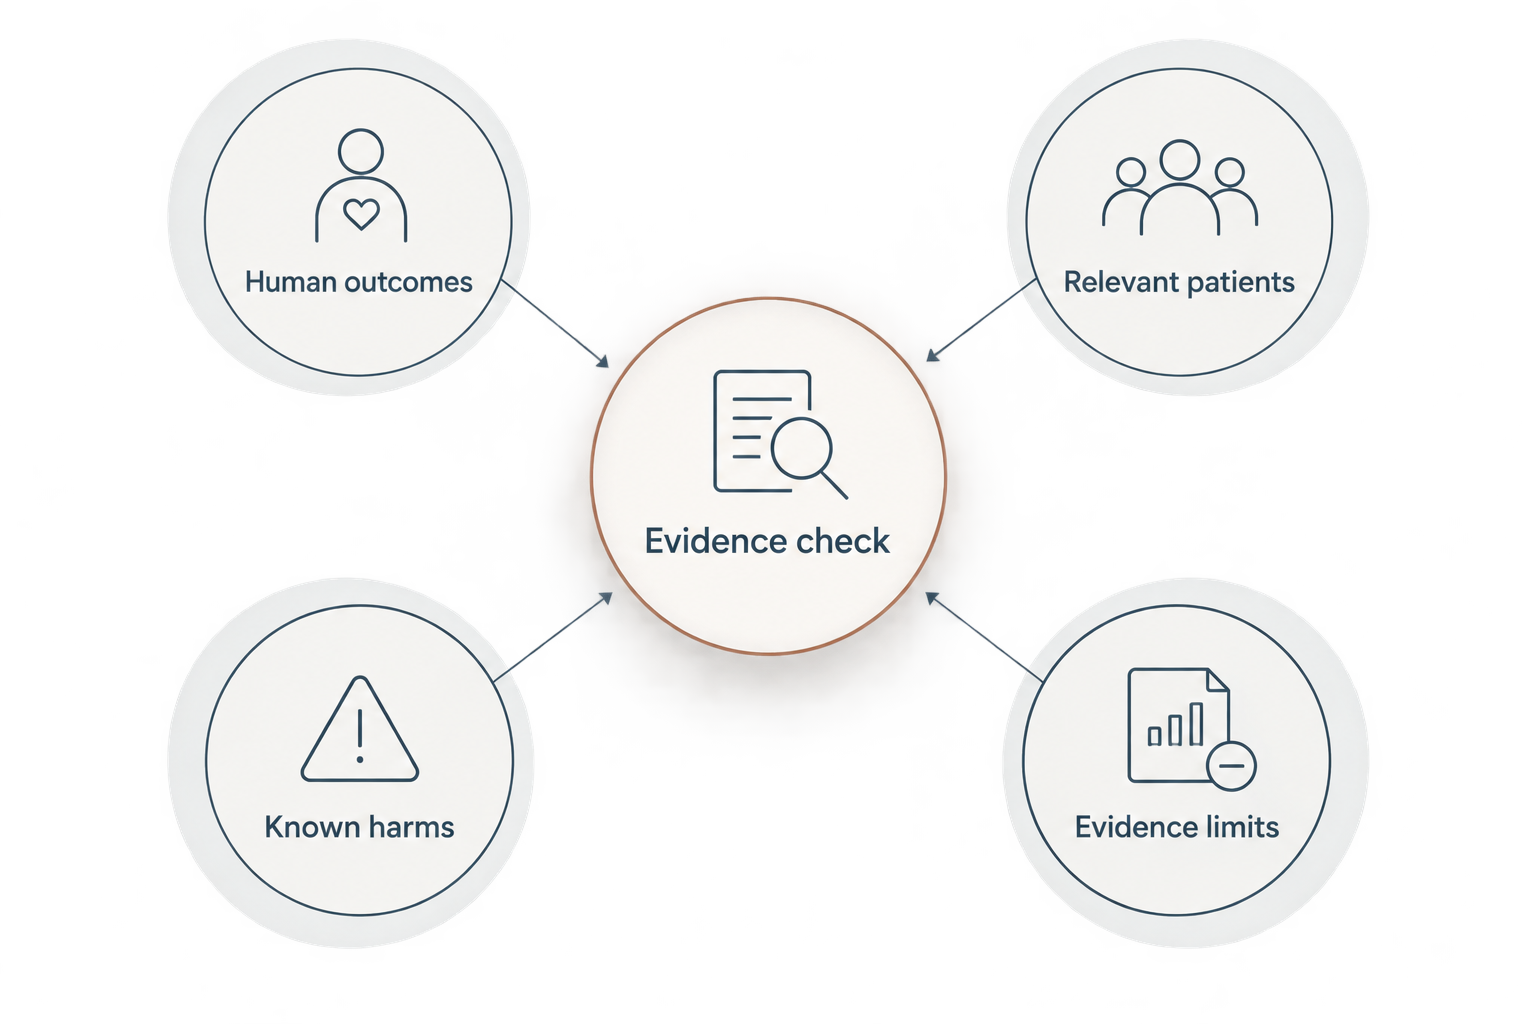
Look for meaningful human benefits and a clear account of harms before accepting a longevity claim.
Longevity approaches at a glance
The order below is a practical priority list, not a head-to-head trial result. Your diagnosis changes the order: smoking cessation takes priority if you smoke, while significantly elevated blood pressure needs direct medical attention.
| Rank and approach | Best for | Evidence-backed benefit | Key limitation |
|---|---|---|---|
| 1. Physical activity | Building a broad health foundation | Fitness, strength and physical function; lower mortality associated with activity | Requires sustained participation and individual adaptation |
| 2. Smoking cessation | Men who smoke | Reduced smoking-related disease and premature death | Nicotine dependence often requires repeated treatment |
| 3. Cardiovascular risk treatment | Men with hypertension or elevated cardiovascular risk | Fewer cardiovascular events with appropriate treatment | Benefits depend on baseline risk and the treatment used |
| 4. Weight management medicines | Men meeting treatment criteria for obesity or overweight with related conditions | Weight reduction; cardiovascular benefit for selected medicines and populations | Not evidence of longer life for every user |
| 5. Testosterone replacement | Men with symptoms and confirmed testosterone deficiency | Improvement in selected deficiency-related symptoms | Not a proven lifespan treatment; requires monitoring |
| 6. Injectable NAD+ | Men considering a proposed anti-aging treatment | No established broad longevity benefit in humans | Uncertain benefit and injection or compounding risks |
1. Physical activity: best longevity foundation for broad health
Regular activity supports cardiovascular fitness, strength and the ability to keep doing everyday tasks. Research consistently associates greater physical activity with lower mortality, while exercise trials demonstrate benefits in fitness and function. That distinction matters: an association is not a guaranteed lifespan gain.
The U.S. Department of Health and Human Services' Physical Activity Guidelines for Americans, published in 2018, recommend at least 150 minutes of moderate-intensity activity per week, plus muscle-strengthening activity on 2 days per week for adults.
Physical activity pros:
- Addresses aerobic fitness and muscular function.
- Can be adapted to your starting ability.
- Complements treatment for several chronic conditions.
Physical activity cons:
- Requires consistency rather than a one-time intervention.
- Symptoms, injuries or unstable disease can require a modified plan.
Best for: Men building a sustainable health foundation. Start within your ability; discuss exertional chest discomfort, fainting or unusual breathlessness with a clinician before increasing intensity.
Verdict: Buy into regular activity—not a promise of guaranteed extra years.
2. Smoking cessation: best for reducing tobacco-related risk
Stopping smoking reduces the risk of premature death and smoking-related disease. The U.S. Surgeon General's 2020 report on smoking cessation documents benefits across cardiovascular disease, cancer and respiratory health.
Counseling and approved cessation medicines offer practical treatment options. Needing another attempt does not mean treatment has failed permanently; nicotine dependence deserves continued care.
Smoking cessation pros:
- Directly addresses a major preventable health risk.
- Benefits health beyond a single laboratory measurement.
- Has established behavioral and medication-based treatments.
Smoking cessation cons:
- Withdrawal and cravings can make stopping difficult.
- Medication selection requires attention to your health history and other prescriptions.
Best for: Men who currently smoke. If that includes you, smoking cessation generally deserves more attention than an elective anti-aging injection.
Verdict: Buy into a supported quit plan; skip the idea that another therapy offsets smoking.
3. Cardiovascular risk treatment: best for documented medical risk
Treating high blood pressure and using cholesterol-lowering medicines when indicated can prevent cardiovascular events. These are separate treatment decisions, not a package every man needs.
Randomized trials support blood-pressure treatment and statins in appropriate patient groups. Your expected benefit depends on factors such as existing cardiovascular disease, blood pressure, cholesterol, diabetes and smoking—not simply your age or interest in longevity.
Cardiovascular risk treatment pros:
- Targets outcomes such as heart attacks and strokes.
- Uses measurable risk factors to guide decisions.
- Allows treatment to be adjusted around response and tolerability.
Cardiovascular risk treatment cons:
- Medicines can cause adverse effects and interactions.
- Treating low-risk people unnecessarily adds burden without the same expected benefit.
Best for: Men with hypertension, established cardiovascular disease or sufficient cardiovascular risk to justify medication. Ask your primary care clinician what risk the proposed medicine treats and how follow-up will work.
Verdict: Buy into indicated risk treatment; skip prescriptions based only on an anti-aging label.
4. Weight management medicines: best for eligible men with obesity
Prescription weight management medicines can help eligible patients lose weight. Evidence for cardiovascular benefit must be tied to a specific medicine and patient population, rather than applied to every product in a category.
The 2023 SELECT trial enrolled 17,604 adults with established cardiovascular disease and overweight or obesity, without diabetes. Semaglutide reduced major adverse cardiovascular events by 20% relative to placebo. That result does not establish longer life for healthy, normal-weight men or prove the same outcome for every weight management medicine.
Weight management medicine pros:
- Can produce clinically meaningful weight reduction.
- Has cardiovascular outcomes evidence for selected treatments and populations.
- Offers a medical treatment option alongside nutrition and activity.
Weight management medicine cons:
- Gastrointestinal adverse effects can affect tolerability.
- Contraindications, nutritional intake and lean-mass preservation need attention.
- Treatment results do not automatically establish a lifespan benefit.
Best for: Men who meet prescribing criteria after an individualized assessment. FDA-approved and compounded products are not interchangeable regulatory categories; compounded semaglutide and tirzepatide are not FDA-approved.
Verdict: Buy only for an appropriate medical indication, not a general longevity promise.
5. Testosterone replacement: best for confirmed deficiency
Testosterone replacement treats testosterone deficiency in appropriately evaluated men. It is not a proven treatment for extending life in men with normal testosterone levels.
The Endocrine Society's 2018 clinical practice guideline recommends diagnosing hypogonadism only when compatible symptoms accompany consistently low testosterone concentrations. Diagnosis generally requires repeat morning testing, with timing and interpretation adapted to clinical circumstances.
Testosterone replacement pros:
- Can improve selected symptoms associated with confirmed deficiency.
- Provides a defined treatment target when the diagnosis is established.
- Allows follow-up of symptoms, testosterone levels and adverse effects.
Testosterone replacement cons:
- Can suppress sperm production and affect fertility.
- Can increase hematocrit and requires monitoring.
- Does not explain or treat every cause of fatigue, low mood or sexual symptoms.
Best for: Men with symptoms and confirmed testosterone deficiency, after a discussion of alternatives, fertility and monitoring. Mensmedicalinstitute provides physician-led testosterone care; the treatment decision still rests on your individual assessment.
Read about coordinating testosterone therapy with primary care before treating hormone care as separate from your broader health.
Verdict: Buy only after a confirmed diagnosis; skip testosterone as a general longevity prescription.
6. Injectable NAD+: best for an evidence-limits discussion
Injectable NAD+ is not a proven longevity treatment. Evidence for broad anti-aging benefit in humans is limited, and changing a biological pathway does not establish that a treatment prevents disability or extends life.
NAD+ has essential roles in cellular metabolism. That established biology is not proof that an injection improves long-term health outcomes, and research on oral precursors cannot automatically establish the benefits of injected NAD+.
Injectable NAD+ pros:
- Addresses a biological pathway that researchers study in aging.
- Offers a specific claim to examine with a physician rather than accepting general anti-aging language.
These are reasons for scientific discussion, not established clinical longevity benefits.
Injectable NAD+ cons:
- Has no established broad human longevity benefit.
- Adds injection-related risks without a proven lifespan benefit.
- Requires attention to sterile preparation and compounding quality.
Best for: Men seeking a candid explanation of the evidence before deciding against or considering treatment. A physician discussion should separate biological plausibility from demonstrated patient benefit.
Verdict: Skip injectable NAD+ as a proven longevity treatment.
How the ranking works
This 2026 ranking prioritizes meaningful human outcomes, relevance to the patient, known harms and honest limits. It does not assign numerical evidence scores or imply that these interventions have been compared directly against one another.
The source anchors are the federal physical activity guidelines, the Surgeon General's smoking cessation report, randomized cardiovascular treatment evidence, SELECT and the Endocrine Society's testosterone guideline. Their findings apply to different populations and outcomes; those boundaries are part of the recommendation.
Which longevity approach should you choose?
Start with your largest established health risk, not the newest treatment name. If you smoke, seek cessation support. If you have hypertension, cardiovascular disease or obesity, discuss the relevant treatment before buying an intervention marketed around biological age.
For a 2026 men's health appointment, bring your medication list, recent laboratory results, symptoms and fertility plans. Ask what condition each proposed treatment addresses, what benefit is realistic, what monitoring is needed and what would justify stopping.
Mensmedicalinstitute offers physician-led men's health care in St. Louis. If you want to discuss testosterone, weight management, ED treatment or NAD+ evidence, call 314-394-1660 without pressure to choose a treatment.
FAQ
What's the best longevity therapy for men in 2026?
There is no single best longevity therapy for every man. Regular activity is a broad foundation, while smoking cessation and treatment of documented cardiovascular risks take priority when those risks are present.
Does testosterone therapy make men live longer?
Testosterone replacement is not a proven lifespan treatment. It treats confirmed testosterone deficiency in appropriately evaluated men and requires discussion of fertility, adverse effects and monitoring.
Are NAD+ injections proven to slow aging?
No. Injectable NAD+ is not a proven longevity treatment, and evidence for broad anti-aging benefit in humans is limited. Its role in cellular metabolism does not establish that injections extend life.
Do weight management injections prevent heart attacks?
Some medicines have cardiovascular outcomes evidence in specific patient groups. SELECT found fewer major cardiovascular events with semaglutide in adults with established cardiovascular disease and overweight or obesity, without diabetes; that finding does not apply automatically to every medicine or patient.
Is a lower biological age score proof that treatment works?
No. A change in a biological age estimate does not by itself prove fewer illnesses, better function or longer life. Ask whether the treatment has demonstrated meaningful health outcomes in people like you.
Should I start testosterone if I feel tired?
Fatigue alone is not enough to diagnose testosterone deficiency. A clinician should assess symptoms, sleep, medicines and other possible causes, then interpret appropriate laboratory testing.
What should I ask before starting a longevity treatment?
Ask what condition the treatment addresses, which human outcomes support it and what harms or monitoring it involves. Also ask how the clinician will decide whether to continue, change or stop treatment.
One last thing
A reassuring laboratory result is not the same as a successful treatment. Before starting anything in 2026, agree with your clinician on the outcome that matters: better function, relief of a diagnosed problem or reduction of an established health risk.
This article provides general education, not individual medical advice. Do not start, stop or change prescribed treatment based on a ranking.